[Disclaimer: Names and all sorts of details have been
changed to maintain confidentiality. As such, any resemblance to real persons,
living or dead, is coincidental.]
“Mr. Maddox is an 86-year-old gentleman with
end-stage congestive heart failure, but you won’t believe it when you walk into
his room. You’ll see what I mean when you meet him, he looks nothing like a congestive heart failure patient, it’s
remarkable!”
A doctor spends her
career as a voyeur to her patient's life – births, birthdays, graduations,
jobs, marriages, divorces. Tragedies. Deaths. Ultimately, even we are powerless
in the face of time and fate. When we accept our impotence, we stop being physicians
and become Charon, ferryman of the dead. We bulwark our patients and their
families as they pick the next turn. And for the token of their trust, we ease
their way across Acheron and Styx.
I spent a recent
morning playing voyeur, rounding on the team’s ICU patients – four individuals
at different distances down the Styx – with the hospice team attending, Dr.
Slate. Two of the ICU patients were in no condition to talk; in fact, they had
been unconscious for several days at least. In a twist of fate, perhaps, these
were the two youngest patients on the list, in their late 40s to early 50s, the
parchment of their life stories prematurely shorn.

Rob was 49, a young
professional with an even younger family. He had been expected to die overnight
after a terminal extubation, but miraculously pulled through the night. Rob had
been in a coma for weeks, missing his daughter's birthday, his wife's promotion.
After those weeks of silence and agony, his wife came to the heartbreaking
decision to let him go. She brought their little girl in one last time to say
good night to her daddy. They kept vigil for hours, watching his breathing
peter out. As the sun rose, the shifts changed. When we rounded, his brother
was in the room with him, watching over his last seconds…minutes…hours, losing
the battle to lung cancer.
Our other young
gentleman, Carl, recently married, had also fallen victim to lung cancer. He
had complete white-out of the right lung, maybe complicated by pneumonia, it
was hard to tell. He was close to failing respiratory therapy when we checked
in on him and had not woken up in days. His wife, sister and mother were coming
in the afternoon for the first of many family meetings. There would be
questions about his diagnosis, his prognosis. His mother would ask if he was in
any pain. His sister would ask what their options were. His wife would ask if
he was ever going to wake up.
No decisions would
be made today.
These first two
patients were non-communicative, obtunded, potentially locked in their own
bodies. Dr. Slate told Rob’s brother that even though he appeared asleep, the
drugs did not put him to sleep. They merely sedated him enough to dull the pain
– he could still hear.
I remember when
Barimama, my grandmother, lost her memory after a stroke and became bedridden
and aphasic. She could only communicate by singing hymns – we were still
granted the gift of her voice, but our voices never reached her again. We had a
diagnosis, but no prognosis. If she was in pain, she could not tell us. She was
awake, but oblivious to the world. We could only stand by as she drifted
farther and farther.
We knew everything,
and yet, nothing. No decisions were made.
“He has an ejection fraction of less than 10 percent.
He also has a history of pulmonary disease, esophageal cancer status-post
resection. His wife of 50 years died two years ago.”
Our other two ICU
patients were older, lonelier gentleman, with no families to turn to. Keith, a
90+ year-old partially deaf man with recurrent colon cancer, was cantankerous
and jonesing to get out of the hospital. “My doctor on TV there, he told me I can
go home today!” he kept eagerly repeating to us. “Get these things offa me and
let me walk outta here now!” His daughter was his health care proxy, and she
had the clarity of knowing his wishes: no life support, only hospice. So sure
enough, we got ‘those things’ off of him and shifted him downstairs to the
hospice unit.
Next door was a
patient who had inexplicably lapsed into a five-day coma, and even more
inexplicably spontaneously woke up a day before the team planned to terminally
extubate him. Sidney was a long-term alcoholic who had broken off ties with his
family years ago. His wife was long-gone, his children long-estranged. Sidney
had no advocate to speak for him – he would become a ward of the state. He was
still intubated, with an unclear degree of comprehension and inevitable,
significant neurological impairment. Of all our patients, his future was
perhaps the most uncertain.

The aftermath of
this ICU morning would leave a little girl without a father, and a new bride
without her husband. Meanwhile, two older gentleman with lives fully lived
would linger on in hospice care, with the scythe of death precipitously
teetering over them, biding its time. It is tempting, and too easy, to try to
weigh one life against another. It is even easier to embrace bitterness and
cynicism when you find the way the scales fall to be unsatisfactory,
"unfair." The key, perhaps, is to leave any sense of justice checked
at the doorstep. The hospital has no room for it, only for empathy and care
regardless of circumstance.
“He requested to become DNR/DNI on this admission,
and is filling out an advanced directive with his daughter this afternoon.”
Our attending
described one of the non-ICU patients as a case of “wrongful life.” Jackie was
a 90+ year-old lady found passed out face-down on her kitchen floor, to our
surprise from drinking too much. “And you think this upstanding little old lady
couldn’t possibly be swizzling alcohol,”
Dr. Slate said. Unbeknownst to EMS, she had a DNR/DNI order, and yet she had
CPR performed, was revived and brought to the hospital. Hence, “wrongful life.”
Now she was debilitated and stuck on life support until and unless her family
decided otherwise.
Situations like this
are not unfamiliar. National news headlines and cable TV themes thrive on
showcasing family drama revolving around terminal care. But it isn't drama.
It's love. Basic human nature dictates, it is always harder to actively choose
to deprive your family member of care than it is to not provide it in the first
place.
Dr. Slate told us it
is our job to empower our patients' families. "Allow them to think of
their role as a protector," he said. "Give them permission to stop us from going overboard and doing more
harm than good." And simultaneously, we should not offer any course of
action that is medically ineffective. False hope is more poisonous even than
inaction.
“He was here at the hospital a couple of weeks ago.
Sounds like there was a med mix-up, that’s why he’s back. Oh, and he has a
device keeping his heart going since 2010, we might need to check the protocol
on it.”
We shifted locations
in the afternoon, where we met our new consult, the 86-year-old gentleman with
heart failure. The social worker was right – we could not believe our eyes when
we walked in the room. The heart failure diagnosis carries with it a certain
picture, of an older patient with significantly edematous extremities, large
body habitus, considerable baseline dysfunction, lying despondently in bed.
But our final patient met none of these descriptions. He looked like a fit,
spry old man, sitting up chatting animatedly with his daughter, with no signs
of edema, nary an ounce of fat to be found. It was hard to believe this was a
man with an ejection fraction almost incompatible with life; if we hadn’t heard
that, we easily would have given him another half-decade at the least.
Mr. Maddox was a
gentleman at peace with his prognosis; he had been granted the years to achieve
that peace. He was content with his life, as long as we could help fix his
shortness of breath enough so he could get back to living it. “I just want to
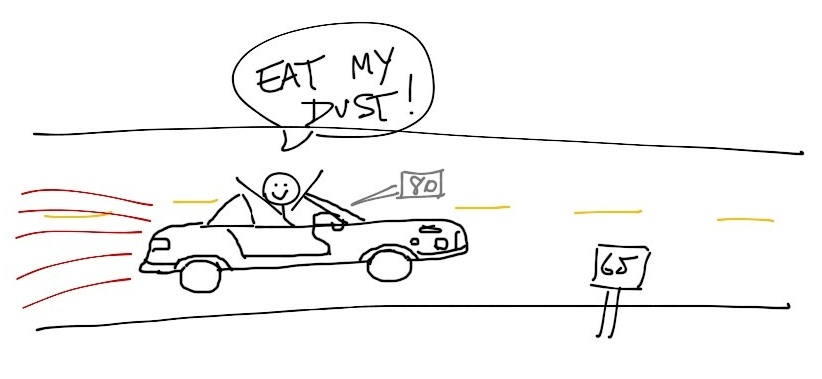
get back out there and drive, doc!” he said. “I drive 80 on 97, I’m nothing
like those old folk on the road!” Dr. Slate turned to Mr. Maddox's daughter and
asked, with a twinkle in his eye, "Would you
get in his passenger seat?" "Oh yes!," she exclaimed.
"And that, students, is the true test," Dr. Slate said.

Where did he want to
drive to? His destinations were perhaps the most telling. Mr. Maddox loved to
cook, and especially loved to cook for his daughter, who worked long shifts. He
would drive meals out to her house, 30 miles away, and it gave him great pleasure
to do so. Even more importantly, though, he paid weekly visits to the nursing
home where his wife spent the terminal five years of her life. “That was our
family, doc,” he said. “Most of them have passed on, too, but there’s five or
six of them still there. I go sit with them for a few hours every week, and it
gives me peace, because it’s where my wife was.”
In many ways, he
reminded me of Barepapa, my grandfather – older, balding, his gentle humor
laced with a tinge of sass, active and independent. Except Mr. Maddox had
managed to retain those traits, while Barepapa progressively lost them in his
five-year battle with Alzheimer’s. The similarities interspersed with the stark
differences had me holding back tears while I was in the room, but he made it
easy to smile with his good-natured acceptance of what was in the pipeline.
I struggled with how
my personal experiences overlapped with so many bits and pieces of the
patients’ lives throughout the day. Everything I saw and heard went through the
filter of my memory – Dr. Slate warned us of it when our day began, yet my
emotional vulnerability managed to sneak up on me. Even so, I cannot help but
embrace it.
We witness many
stages of death in our time on the wards. But the same vulnerability that
brings tears to our eyes and a pang to our gut also provides us a lens beyond
death to humanity, individuality and conviction. For that, a tender heart is a
small price to pay.
"Anyway: I am not blessed or merciful. I'm just
me. I've got a job to do and I do it. Listen: even as we're talking, I'm there
for old and young, innocent and guilty, those who die together and those who
die alone. I'm in cars and boats and planes, in hospitals and forests and
abattoirs. For some folks death is a release and for others death is an
abomination, a terrible thing. But in the end, I'm there for all of them."
-Death,
Sandman #30: "Façade" (Neil Gaiman)
 Identity.