Showing posts with label med school. Show all posts

Sunday, January 26, 2014

Dialects of love

[Disclaimer: Names and all sorts of details have been changed to maintain confidentiality. As such, any resemblance to real persons, living or dead, is coincidental.]

7:30 a.m., reporting for duty to the intensive care unit. I was just two months shy of finishing third year, and thought myself immune to the beeps and alarms that passed for signs of life in the hospital.

My fellow took a break from pre-rounding to assign me a patient. No new admissions had come in for quite some time, so she instead assigned me a young gentleman, Coby, who had been in the ICU for almost two months.

I hurriedly jotted down an abbreviated clinical introduction – student, sudden collapse, intracranial bleed, herniation, not arousable – and an even more abbreviated social introduction – dedicated family.

Dedicated family. Close-knit. One could mistakenly think we minimize their depth of commitment with our sparse words. But the fellow’s words were accompanied by a note of grief, a glance toward Coby’s room to reassure herself the family was okay, not flagging someone down in a panic. But the glance was reflexive – his room was around the corner, out of sight. She said, “Talk to them, and answer their questions if you can. But never assume.”

I steeled myself to approach Coby and his family, not out of apprehension in interacting with them but because I could not predict their response to me and my own response to the situation. As a medical student, I had little exposure to the trials of the ICU, abode to some of the sickest patients in the hospital. What comfort could I, an inexperienced physician-in-training possibly offer a tortured family? I was young enough to be their child. Would they view me as insolent? Presumptuous? The stark white walls of the hallway to his room offered no solace, as if mocking my supposed “immunity” to the sounds they channeled to my ears.

My apprehensions were unrealized, at least for that first entry into his room. He was alone, harsh vent-supported breaths rippling from his trach collar, even as the cardiac monitor beeped at a deceptively regular rhythm. But before I saw Coby, I saw the walls of his room, plastered floor-to-ceiling with posters, cards, sports logos, a fraternity sweatshirt. His friends told him to hurry up so they could get back to their soccer tourney. His niece was waiting to show him her newest toy. There were colored pencil drawings of mountain ranges and rainbows, a cup of coffee, a rainy day. In his silence, the colors on the walls screamed their love.

Expressions of love lurk in many nooks and crannies of the hospital, not always with bright colors and words of sentiment. Down the hall from Coby’s room, an elderly lady’s daughters posted an austere sign on the IV pole by her bedside: “Say ‘Hi’ to me…I cannot see.” Anytime someone entered the lady’s room, she strained her neck in indecision, unsure which direction to turn her head. Some staff were cognizant and lent her the thread of their voice. Others remained painfully invisible, dismissive of the sign and silent in their breach of social contract.

Two floors below on another ward, the headboard above a comatose patient’s bed is carpeted in words of faith, in stark black and gray and white. Some are methodically stenciled in pencil. Others are sketched in permanent marker, as if to impart endurance. John 10:10. Exodus 15:26. Luke 1:37. Jehovah-Rapha: I am the Lord your physician.

When I graduated from college, my best friend’s mother gifted me a shivling, representing the infinity of creation, the cycle of life. “May it guide your healing hands,” she said. I wear it as my own token from a loved one, in the hospital where balloons and stuffed animals offer affection in proxy. 

I spent several minutes more than I had been granted standing by Coby’s bedside. The sobering faith adorning his walls sank under my skin. His wrist felt clammy under my one hand, as my other hand reached up to grip my pendant. The smooth, dry surface was at odds with the dampness hanging heavily in the room – from his skin, from his vent. 

His family returned to the room. Their lips moved interminably in silent prayer, loath to break their cadence of insistent hope for a green stranger. His aunt adjusted the temperature on his heated blanket, and meticulously jotted numbers in her pocket notebook. His mother stood by his pillows with a wash towel in hand, gently wiping the drool he could no longer control. His father stood watch at the foot of the bed, doggedness in his spine and weariness in his shoulders. 

And I found myself backing into the corner, head bent, eyes closed. The colors from his walls danced behind my eyelids as I yearned for the solace I had sought to provide. I did not disturb their vigil with empty words, for I had no answers, only questions.

---

Please share your stories/thoughts/comments/criticism below.

Sunday, April 7, 2013

80 on 97 at 86.5


 [Disclaimer: Names and all sorts of details have been changed to maintain confidentiality. As such, any resemblance to real persons, living or dead, is coincidental.]

“Mr. Maddox is an 86-year-old gentleman with end-stage congestive heart failure, but you won’t believe it when you walk into his room. You’ll see what I mean when you meet him, he looks nothing like a congestive heart failure patient, it’s remarkable!”

A doctor spends her career as a voyeur to her patient's life – births, birthdays, graduations, jobs, marriages, divorces. Tragedies. Deaths. Ultimately, even we are powerless in the face of time and fate. When we accept our impotence, we stop being physicians and become Charon, ferryman of the dead. We bulwark our patients and their families as they pick the next turn. And for the token of their trust, we ease their way across Acheron and Styx.

I spent a recent morning playing voyeur, rounding on the team’s ICU patients – four individuals at different distances down the Styx – with the hospice team attending, Dr. Slate. Two of the ICU patients were in no condition to talk; in fact, they had been unconscious for several days at least. In a twist of fate, perhaps, these were the two youngest patients on the list, in their late 40s to early 50s, the parchment of their life stories prematurely shorn.

Rob was 49, a young professional with an even younger family. He had been expected to die overnight after a terminal extubation, but miraculously pulled through the night. Rob had been in a coma for weeks, missing his daughter's birthday, his wife's promotion. After those weeks of silence and agony, his wife came to the heartbreaking decision to let him go. She brought their little girl in one last time to say good night to her daddy. They kept vigil for hours, watching his breathing peter out. As the sun rose, the shifts changed. When we rounded, his brother was in the room with him, watching over his last seconds…minutes…hours, losing the battle to lung cancer.

 Our other young gentleman, Carl, recently married, had also fallen victim to lung cancer. He had complete white-out of the right lung, maybe complicated by pneumonia, it was hard to tell. He was close to failing respiratory therapy when we checked in on him and had not woken up in days. His wife, sister and mother were coming in the afternoon for the first of many family meetings. There would be questions about his diagnosis, his prognosis. His mother would ask if he was in any pain. His sister would ask what their options were. His wife would ask if he was ever going to wake up.

No decisions would be made today.

These first two patients were non-communicative, obtunded, potentially locked in their own bodies. Dr. Slate told Rob’s brother that even though he appeared asleep, the drugs did not put him to sleep. They merely sedated him enough to dull the pain – he could still hear.

I remember when Barimama, my grandmother, lost her memory after a stroke and became bedridden and aphasic. She could only communicate by singing hymns – we were still granted the gift of her voice, but our voices never reached her again. We had a diagnosis, but no prognosis. If she was in pain, she could not tell us. She was awake, but oblivious to the world. We could only stand by as she drifted farther and farther.

We knew everything, and yet, nothing. No decisions were made.

“He has an ejection fraction of less than 10 percent. He also has a history of pulmonary disease, esophageal cancer status-post resection. His wife of 50 years died two years ago.”

Our other two ICU patients were older, lonelier gentleman, with no families to turn to. Keith, a 90+ year-old partially deaf man with recurrent colon cancer, was cantankerous and jonesing to get out of the hospital. “My doctor on TV there, he told me I can go home today!” he kept eagerly repeating to us. “Get these things offa me and let me walk outta here now!” His daughter was his health care proxy, and she had the clarity of knowing his wishes: no life support, only hospice. So sure enough, we got ‘those things’ off of him and shifted him downstairs to the hospice unit.

Next door was a patient who had inexplicably lapsed into a five-day coma, and even more inexplicably spontaneously woke up a day before the team planned to terminally extubate him. Sidney was a long-term alcoholic who had broken off ties with his family years ago. His wife was long-gone, his children long-estranged. Sidney had no advocate to speak for him – he would become a ward of the state. He was still intubated, with an unclear degree of comprehension and inevitable, significant neurological impairment. Of all our patients, his future was perhaps the most uncertain.

The aftermath of this ICU morning would leave a little girl without a father, and a new bride without her husband. Meanwhile, two older gentleman with lives fully lived would linger on in hospice care, with the scythe of death precipitously teetering over them, biding its time. It is tempting, and too easy, to try to weigh one life against another. It is even easier to embrace bitterness and cynicism when you find the way the scales fall to be unsatisfactory, "unfair." The key, perhaps, is to leave any sense of justice checked at the doorstep. The hospital has no room for it, only for empathy and care regardless of circumstance.

“He requested to become DNR/DNI on this admission, and is filling out an advanced directive with his daughter this afternoon.”

Our attending described one of the non-ICU patients as a case of “wrongful life.” Jackie was a 90+ year-old lady found passed out face-down on her kitchen floor, to our surprise from drinking too much. “And you think this upstanding little old lady couldn’t possibly be swizzling alcohol,” Dr. Slate said. Unbeknownst to EMS, she had a DNR/DNI order, and yet she had CPR performed, was revived and brought to the hospital. Hence, “wrongful life.” Now she was debilitated and stuck on life support until and unless her family decided otherwise.

Situations like this are not unfamiliar. National news headlines and cable TV themes thrive on showcasing family drama revolving around terminal care. But it isn't drama. It's love. Basic human nature dictates, it is always harder to actively choose to deprive your family member of care than it is to not provide it in the first place.

Dr. Slate told us it is our job to empower our patients' families. "Allow them to think of their role as a protector," he said. "Give them permission to stop us from going overboard and doing more harm than good." And simultaneously, we should not offer any course of action that is medically ineffective. False hope is more poisonous even than inaction.

“He was here at the hospital a couple of weeks ago. Sounds like there was a med mix-up, that’s why he’s back. Oh, and he has a device keeping his heart going since 2010, we might need to check the protocol on it.”

We shifted locations in the afternoon, where we met our new consult, the 86-year-old gentleman with heart failure. The social worker was right – we could not believe our eyes when we walked in the room. The heart failure diagnosis carries with it a certain picture, of an older patient with significantly edematous extremities, large body habitus, considerable baseline dysfunction, lying despondently in bed. But our final patient met none of these descriptions. He looked like a fit, spry old man, sitting up chatting animatedly with his daughter, with no signs of edema, nary an ounce of fat to be found. It was hard to believe this was a man with an ejection fraction almost incompatible with life; if we hadn’t heard that, we easily would have given him another half-decade at the least.

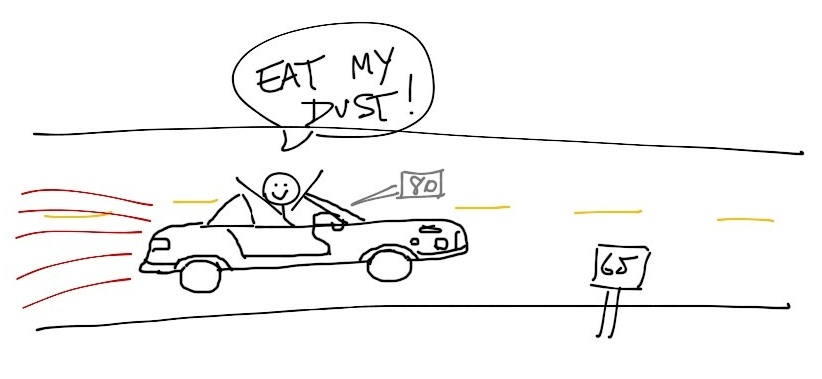
Mr. Maddox was a gentleman at peace with his prognosis; he had been granted the years to achieve that peace. He was content with his life, as long as we could help fix his shortness of breath enough so he could get back to living it. “I just want to get back out there and drive, doc!” he said. “I drive 80 on 97, I’m nothing like those old folk on the road!” Dr. Slate turned to Mr. Maddox's daughter and asked, with a twinkle in his eye, "Would you get in his passenger seat?" "Oh yes!," she exclaimed. "And that, students, is the true test," Dr. Slate said.
 Where did he want to drive to? His destinations were perhaps the most telling. Mr. Maddox loved to cook, and especially loved to cook for his daughter, who worked long shifts. He would drive meals out to her house, 30 miles away, and it gave him great pleasure to do so. Even more importantly, though, he paid weekly visits to the nursing home where his wife spent the terminal five years of her life. “That was our family, doc,” he said. “Most of them have passed on, too, but there’s five or six of them still there. I go sit with them for a few hours every week, and it gives me peace, because it’s where my wife was.”

In many ways, he reminded me of Barepapa, my grandfather – older, balding, his gentle humor laced with a tinge of sass, active and independent. Except Mr. Maddox had managed to retain those traits, while Barepapa progressively lost them in his five-year battle with Alzheimer’s. The similarities interspersed with the stark differences had me holding back tears while I was in the room, but he made it easy to smile with his good-natured acceptance of what was in the pipeline.

I struggled with how my personal experiences overlapped with so many bits and pieces of the patients’ lives throughout the day. Everything I saw and heard went through the filter of my memory – Dr. Slate warned us of it when our day began, yet my emotional vulnerability managed to sneak up on me. Even so, I cannot help but embrace it.

We witness many stages of death in our time on the wards. But the same vulnerability that brings tears to our eyes and a pang to our gut also provides us a lens beyond death to humanity, individuality and conviction. For that, a tender heart is a small price to pay.


"Anyway: I am not blessed or merciful. I'm just me. I've got a job to do and I do it. Listen: even as we're talking, I'm there for old and young, innocent and guilty, those who die together and those who die alone. I'm in cars and boats and planes, in hospitals and forests and abattoirs. For some folks death is a release and for others death is an abomination, a terrible thing. But in the end, I'm there for all of them."
-Death, Sandman #30: "Façade" (Neil Gaiman)

Sunday, October 7, 2012

Moment for life


[Disclaimer: All patients appearing in this are fictitious. Any resemblance to real persons, living or dead, is coincidental.]

No week is ordinary on an inpatient psychiatric ward, but this one stood out.

We received notice of her arrival at morning sign-out from the charge nurse. "Mid-20s female with a history of bipolar disorder with psychotic features, self-reported to the psych ER with suicidal ideation and depressed mood. History of depression, self-reported bipolar-affective disorder, drug abuse." With each of those descriptors I added a mental characterization - unstable, psychotic, jaded, distrustful. Then again, a self-reported history of "the bipolar" in Baltimore frequently means no more than a means to a disability check.

Shantel turned out to fit all those descriptors, yet bore little resemblance to the caricature I had painted.

We sat in the cramped conference room for her initial interview, facing off against her over an unforgiving metal table. Her long, tapered fingers beat a staccato rhythm, a conspicuous, irritable edge to her movements. Faint tear marks tracked down her cheeks, bracketing the false bravado in her tremulous smile. She caved in as we introduced ourselves, folding into the hard chair and desperately trying to keep her pride and personhood from shattering against our white coats.

We asked her questions.
"How have you been?"
"Tell us a little bit about yourself."

She twisted her fingers, played with her hair, wove convoluted sentences - stuffing with nothing holding them together.
"I'm eating like I'm pregnant, but I ain't pregnant."
"They got me, but then I went away and they didn't get me anymore, but I read a book and I knew where to go, until I found some apples."

But ten minutes in, when my resident's patience was thinning and I was leaning down to retrieve my pen, Shantel floored me with a sharp look of tempered fear. Her raspy voice tripped over the words, still pressured but ringing with sincerity. "I committed myself. I gotta be better. For me. For my little girl. For them. Else we all get hurt." She sat a few inches taller than me, but as she spoke, she bent with her words, a sapling valiantly fighting its own youth and fragility.

Her wiry frame quivered with her dreams for the future, simple ones - stay safe, be healthy, raise a family - confined by the boundaries of her paper-thin skin and see-sawing psyche. The confession attenuated her hesitation, but not her paranoia, and the rest of our week was filled with the color of her personality and a litany of complaints, both from our staff and our elusive patient.

Shantel keeps flirting with the young male patients.
They hate me. They're putting stuff in my food. It's yellow!
She started gyrating to Nicki Minaj in the common area this morning.
I'm staying in my room today. They keep glaring at me, I can see the devil in their eyes.

None of the contact numbers she initially gave us worked. One was an anonymous voicemail, one was connected to a construction company, and the last was to a sex hotline - an interesting explanation to human resources…

When I finally tracked down the aunt who had raised her, she had one piece of advice for us. "You keep her locked down, you hear? She runs. That's all she knows to do, and she's damn good at it!"

Shantel's elopement history spoke for itself. She was damn good at it. She had escaped from any number of institutions and programs in a 30-mile radius, sometimes repeatedly - by removing AC units, stealing nurses' keys, scrambling through air vent systems, sneaking out on the food cart.

She acted half her age and looked twice it, no insignificant disparity for a woman in her mid-20s. I could have wrapped my fingers twice around her wrist. Her face was gaunt, her cheeks sunken under the weight of her illness and her struggles.

I checked in on her a few times a day. The first time, she set the tone with a warning, "I have a gift where I can see through what people are saying. I was a crack baby." 

"Hey Shantel, how are things going today?"
"Everything hurts - my legs, my calves, my arms."
"Is anything else hurting you?"
"My feelings."

Her childish innocence repeatedly reared its unforgiving head, as if she was checking whether we were paying attention.

"How are you feeling today?"
"I don't feel the sincerity or the loyalty I should."

"We heard from the staff that you wanted to stay in your room today, is everything okay?"
"They act like they're scared or disgusted. They treat me like I'm strange or different, and I don't like that."

"Do you want to hurt yourself or anyone else?"
"I don't know if I want to live or die."

"What do you like to do?"
"I like to write poems, and collect knives."
"Why?"
"Someone hurt me a lot, when I was little. Beat me up. Had sex with me. The poems help my head, and the knives help my body."

The inherent power imbalance in our relationship, she was well aware of. But she never learned the extent to which we had managed to even the scales of knowledge of her past. What we knew of it, we learned from the one call to her aunt, or from the three-inch stack of past records painstakingly obtained from her array of psychiatric visits to dozens of individuals and institutions, a novel in its own right.

But even though we had thousands of scraps of her timeline, they were constantly overlapping, never lining up. The sad truth about inpatient psychiatry, it is a layover toward a final destination. We never had the chance to walk through her past with her. We would have had just enough time to break down her defenses, with none to spare toward building a safety net for the released demons.

In her case, the destination we sought, and her social worker managed to secure, was a housing program for patients requiring psychiatric support. Given her penchant for running, the social worker even ensured door-to-door service. A representative from the program came to accompany Shantel from the locked entrance of the inpatient unit to the watchful eye of the house caretaker.

Three weeks later, our team's social worker flagged me down from the opposite end of a long hallway. The distance felt interminable, watching her face transform from exaggerated attention-seeking to apologetic and pitying. She rarely flagged me down, and even more rarely for good news. I was not hardened enough yet for the news she was about to hesitatingly deliver to me - news I had unknowingly brought upon myself.

"They IDed a Jane Doe on one of the autopsy tables at the morgue yesterday."

She paused. I wonder what my face gave away. Shock? Grief? Resignation? The last one seared through me, an unforgivable burn. I forced myself to prompt her for the name, fingers crossed behind my back and toes crossed inside my shoes. Perhaps hearing it would be my absolution for so readily losing faith.

"Shantel. She ran away."

Her autopsy results were not due back until after my time on the ward completed. But the superficial cause of death was somewhat irrelevant. Ultimately, the driving force would be irreversibly tangled with her mental illness, her drug habit and her naïve immaturity.

I only felt increasingly powerless as the weeks carried forward. Nothing I wanted to take from this experience was helpful to my patients during their fleeting sojourns with us, or so I felt. I still did not have the time to build a meaningful therapeutic relationship with them, did not have the breadth of resources to hold their hands through a torturous walk down memory lane.

What I did learn, albeit indirectly and over a painful month of second-guessing, was the power of the psych ER and the inpatient ward as a front line of defense. For all that it felt like we were failing our patients, we served another purpose - tracking them to the long-term therapy that would help rehabilitate them. Maybe we gave Shantel a few extra weeks she may not have had otherwise. Maybe in the time she spent with us, we validated her experiences and her sense of self.

Our profession finds mileage in the weightlessness of hope. Perhaps even more so in a field where the damages born are invisible and the wounds take years to scar. 

Monday, September 10, 2012

Noose of suspicion

“I prefer credulity to skepticism and cynicism for there is more promise in almost anything than in nothing at all." - Ralph Perry
Friday afternoon of Grand Prix weekend. The city mayor has issued a decree - all persons found prone on the streets of the city are to be transported by ambo to the nearest hospital within two miles headed away from the racing streets. The rule seemed laughable at the time. Prone persons in the city streets? The ERs would be flooded.

Our patient lucked out, thanks to the decree. The circumstances of her pick-up and arrival were unclear, but since she was nearly full-term in pregnancy, she wound up in L&D's triage, completely unconscious and unarousable. Paramedics must have found an ID, because we had a name, leading to scant records in the system from a past ER visit or two, but little else. No prenatal records, because she didn't see any of our hospital-affiliated OB's for care. No significant demographic or psychosocial information. A mystery heightened by her incapacitated state.

Concern was mounting, however, because her baby was as unresponsive on its heart monitor as she was, and so the debates began. How long did we wait for the baby to wake up before we took her for an emergency c-section? How long did we wait for the mother to wake up and face our inquisition? Should we attempt an overdose-reversing therapy in the interim?

She had no autonomy of decision, because she was asleep and had no advocates, no one we could track down. She had a nurse who was increasingly concerned for the baby. She had a resident who was convinced she was a druggie, intent on getting a high even if it meant screwing her baby over along the way. She had another resident with a cool head, patience and an iota of faith. And all this before she awoke and had a chance to speak even a word in her own defense - not that it made a difference even when she did.

Resident #1 kept evolving her own opinions without ever meeting the patient. Meanwhile, the nurse, resident #2 and I spent 45 minutes trying to stimulate the infant on the monitor and on ultrasound. We managed to engage the patient in spurts of awareness, and piece together haphazard segments of her last 12 hours. Her urine toxicology came back positive for a handful of things, some of which she fessed up to and others that elicited a palpable, visceral shock.

Her grip came to bear on my wrist as tightly as the fetal heart monitor snapped around her abdomen, almost cutting off circulation. What was wrong with her baby? What had she done? In the months of her struggle with psychiatric issues, staying off medication to avoid harm to her baby; in the months of abandonment by her family; in the months of terror, tears and confusion; she had lost her way, more helpless than willfully destructive. And here in the hospital, where she should have been able to expect support and unbiased care, she had to fight not only against her psyche, but also against the ill-informed preconceptions of her own caretakers.

Even as mom woke up and became increasingly aware of her situation, the baby insisted on sleeping in, and eventually dragged its mom into the OR for an emergency c-section. Medically speaking, the situation ended as positively as one could hope - the c-section proceeded without any complications, and the baby came out looking fantastically healthy and alert. Now mom was left to deal with the fall-out, with the questions from social work and CPS.

Everyone was predisposed to believe the worst. Clearly she was a drug-addled woman, unfit to be a mother, callous to her baby's needs, constantly on the prowl for the next high. Never mind that she was scared to death of the possible harm she had caused her kid. Never mind that she was terrified of losing her baby to the system. Never mind that she felt demeaned because no one had the courtesy to treat her like a person and keep her informed - the most basic of courtesies, one could argue, when we hold all the cards and she holds none.

Who will advocate for her? The nurse who is annoyed by the barrage of questions from a perceived irresponsible mother? The staff who discount her incisional pain as the lure of a drug seeker?

I only have unfounded theories about what fosters this unshakable suspicion. Some have probably been burned countless times in the past for giving the benefit of the doubt, and having patients take advantage of their empathy. Some have lost their integrity of faith, maybe had it beaten out of them by the job or job culture. Some are just predisposed to cynicism from the beginning, and they are perhaps the ones we can never sway. I keep hoping I can find the necrosed root and chop it off, even while recognizing it's an impossible feat. At the least, I hope nothing can quash my idealism, however naïve it may prove to be.

Never have I felt this frustration more keenly. We have all, since starting med school, dreamed of the day when we are capable of assisting the nurses, putting in orders, answering patients' queries, and have constantly felt the pang of disappointment when we cannot fulfill any of those. But for the first time this weekend, I felt the hollow sink of failure, confusion from standing alone in my opinion of my patient's needs.

Was I a sucker for empathizing with her helplessness, for believing in her commitment to love and nurture her child? Honestly, the answer to that question is irrelevant.

This job is not easy. Of all the patients we will meet who struggle with addiction, probably 80 percent of them will attempt to exploit us for pain killers. To some degree, they cannot help it, nor can they recognize their helplessness; that task falls to us. Of that 80 percent, maybe 60 percent will claim they want to quit, they need help. And of that 60 percent, maybe 10 percent will mean it. It might start with 2 days clean, then 2 weeks, and for a handful of them, maybe it will graduate to 2 years, or even 20.

But we have no way of knowing who that handful will be, and who are we to project a perceived fate onto anyone? That falls outside of our purview.

We should be the torchbearers of faith, believing that any person walking through our doors could be among the handful. And if we nurture them as such, maybe that handful will grow. If we lose faith in them, who will they hang their dreams on? 

Thursday, September 8, 2011

Kick in the Pants

Med school started 'forreal forreal' yesterday, with Host Defenses and Infectious Diseases. So far, it is busting our chops big time. And it's barely been two days.

Exam day Tuesday didn't go quite as Ian had hoped. And tragically, this is Ian's new reality:


In other news, things I've learned so far:

The only way to get better is to get wayy worse first

And there is a profound revelation reflected in Ian's shaved head
(yes, his nose is actually that hooked. Peer closely the next time you see him; it'll creep him out)

This is kind of turning into the 'Ekta and Ian' show, isn't it? Only good things can come of it.


Monday, September 5, 2011

Don't Forget the Confetti

Today we are featuring some guest art by [drumrollllll] IAN P! Dutifully doodled on the last day of lectures before our long weekend, between the hours of 1000 and 1200. Make of that what you will.

Every exam day, Ian comes with high hopes -- of gifted A's, laptops in the air, and confetti:

 And tragically, every exam day, those hopes are dashed.

Hope springs eternal.